We're changing the way Sapphire looks
Same platform, new visual identity. Learn more: Sapphire is becoming NHMRC Grant Management System.
We're changing the way Sapphire looks
Same platform, new visual identity. Learn more: Sapphire is becoming NHMRC Grant Management System.
Engagement is a relationship built on trust and integrity
Hunt (Hunt 2013) describes engagement as a relationship built on trust and integrity: 'it is a sustained relationship between groups of people working towards shared goals…a deliberative and negotiated process, which moves beyond information giving or consultation.
Archaeological evidence demonstrates that Aboriginal and Torres Strait Islander Peoples have been living in this land we now call Australia for at least 65,000 years. During this time communities developed sophisticated knowledge systems for managing the environment and understanding, interpreting and communicating information.These knowledge systems underpinned a thriving culture that began being dismantled from the time of colonisation (Ball 2015).
Since British colonisation, Aboriginal and Torres Strait Islander Peoples* have experienced successive waves of intergenerational trauma (Atkinson, 2013) and been extensively studied by groups who have had more power and privilege. Until recently researchers have used different knowledge systems that have systematically excluded Indigenous people from having an active voice (Laycock, Walker et al 2011). At the same time there has been simultaneous disregard — and in many cases — active suppression of Aboriginal knowledge being generated, expressed and passed on. This has led to many distorted versions of understandings ‘about’ Indigenous people that reflect non-Indigenous values, beliefs and prejudices (Laycock, Walker et al 2011).
Many of these distorted perceptions have led to a dominant ‘deficit discourse’ that represents people or groups in terms of deficiency, absence, lack or failure. This has happened particularly within the health sector (Fogarty, Lovell et al 2018).
Additionally, holistic Aboriginal and Torres Strait Islander understandings of health and wellbeing are not often reflected in existing research:
Aboriginal health does not just mean the physical wellbeing of an individual, but refers to the social, emotional, and cultural wellbeing of the whole community. For Aboriginal people this is seen in terms of the whole-life-view. Health care services should strive to achieve the state where every individual is able to achieve their full potential as human beings, and must bring about the total wellbeing of their communities.NACCHO, quoted in Gee, Dudgeon et al 2014
Aboriginal and Torres Strait Islander Peoples and communities each have their own established and respected values and protocols, and unique ways of expressing their different values. Figure 1 outlines six core values identified as being important to all Aboriginal and Torres Strait Islander Peoples: spirit and integrity, cultural continuity, equity, reciprocity, respect, and responsibility.
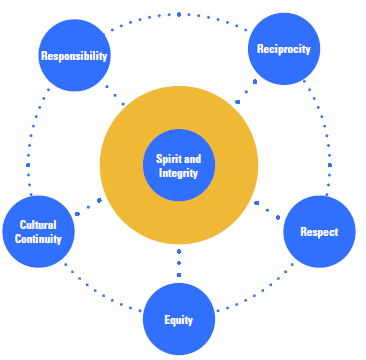
Sourced from: Ethical conduct in research with Aboriginal and Torres Strait Islander Peoples and communities: Guidelines for researchers and stakeholders 2018 and Keeping research on track II 2018.
This has important implications for guideline developers who are responsible for developing the guidelines in a way that empowers Aboriginal and Torres Strait Islander Peoples, through ownership of the guideline development process, by:
The objective of this module is to give practical advice to guideline developers about how Aboriginal and Torres Strait Islander people need to be involved in the development of guidelines about health issues that impact their communities. This module should be read together with the Equity, Consumer involvement, Engaging stakeholders, and Guideline development group modules. The module also supports NHMRC resources that have been developed for the research sector: Keeping research on track II, Ethical conduct in research with Aboriginal and Torres Strait Islander Peoples and communities and Road map 3.
Before engaging with Aboriginal and Torres Strait Islander communities it is worthwhile taking time to reflect on your own values, principles and beliefs; and to understand the way our shared history impacts on relationships between Aboriginal and Torres Strait Islander and non-Indigenous Australians today.
A useful concept to describe a genuine two-way knowledge sharing is embodied in the Yolŋu metaphor of Ganma. Ganma is a Yolŋu word for a lagoon where saltwater meets fresh and the new knowledge that results from this blending, without the loss of history or integrity in the process (Laycock, Walker et al. 2011). It is an important process to recognise during interactions across the lifecycle of guideline development.
If initial scoping investigations and consultation with peak bodies suggest the topic has specific implications for Aboriginal and Torres Strait Islander Peoples — for example, implications related to achieving equity of health outcomes — NHMRC suggests appointing an Aboriginal and/or Torres Strait Islander person as the chair or co-chair of the guideline development group. This is in addition to other Aboriginal and Torres Strait Islander representatives. A general principle should be - the greater the implications for a specific group, the greater the need for engagement, involvement and leadership from that group (see Case study 1 in the downloadable attachment).
If you are developing guidelines about a general health issue that may also impact Aboriginal and Torres Strait Islander Peoples, then at least two Aboriginal and Torres Strait Islander representatives should be included on the development group. Doing this makes it easier for members of a non-dominant group to have a voice.
Some checklists may help determine whether you need to target your guideline for Aboriginal and Torres Strait Islander Peoples or whether you might want to frame it around equity-sensitive questions (Welch 2017, Akl 2017). These will be important to consider at the beginning of the guideline development process as they may have implications for the selection of the chair or guideline development group members.
NHMRC asks Australian guideline developers to ensure that issues relevant to Aboriginal and Torres Strait Islander Peoples — such as particular risks, treatment considerations or sociocultural considerations — are identified and described.
There are a number of Australian resources available to help you scope relevant issues and determine priorities including:
It is important for guideline developers to note that relevant Aboriginal and Torres Strait Islander perspectives and worldviews may not be included in the academic literature. Think critically when exploring data or examining results such as whether Aboriginal and Torres Strait Islander people have been part of the data collection or design of studies, or how the data sets were informed.
Engagement is undertaken with an understanding of the historical, cultural and social complexity of specific local or regional contexts (Hunt 2013). Cultural security, safety and awareness are essential for working effectively with communities (Coffin, Drysdale et al. 2008) (Alcohol and Drug Foundation) and providing a culturally safe environment is critical.
Hurried, one-off consultations that are organised without direct input from communities and through community structures, do not work (Hunt 2013). Relationships take time to develop and so it is important to start building them from the beginning of the guideline project, and to maintain them throughout the process. It is important that Aboriginal and Torres Strait Islander representatives lead the conversation and focus on respectful and deep listening (Dadirri) (West, 2012).
It is important to use a ‘strengths-based’ lens in discussions recognise the resilience and assets of a community — knowledge, skills, networks, extended family and cultural identity. A strengths-based lens also incorporates a holistic approach to wellbeing; the social determinants of ‘good health’; as well as protective factors (Fogarty, Lovell et al. 2018).
Recognising the diversity of communities is an important consideration for guideline developers when seeking representatives for the guideline development group. This includes recognising diversity and differences in urban, rural or remote living, gender, class, language, sexuality and disability.
Although it is recommended that the guideline development group has at least two Aboriginal and Torres Strait Islander people as members, they cannot be expected to represent the views of all Aboriginal and Torres Strait Islander Peoples. Other mechanisms may be needed such as establishing an expert advisory committee to specifically address issues relevant to Aboriginal and Torres Strait Islander Peoples (see Case study 2 Clinical Practice Guidelines: Pregnancy Care 2018 in the downloadable attachment).
Useful organisations to approach for potential representatives could include:
Ensuring that all representatives of a guideline development group feel comfortable and supported to present their views is critical to its functioning. It is important to recognise that styles of communication may be different from dominant culture communication styles, and to ensure that a culturally safe environment is provided for the group.
The Guideline development group module has more information about asking organisations to nominate a representative, preparing group members for their role and compensating representatives for their time and efforts.
Because there are structured knowledge systems around how Aboriginal and Torres Strait Islander knowledge is passed on, seeking community views must be done with the permission from community knowledge-holders (see the Useful Resources section below for information to start this process).
There are often local protocols to consider when engaging with Aboriginal and Torres Strait Islander communities including different kinship relationships and the laws governing social interactions. Take the time to learn about local history and traditions including traditional names for the lands and languages and the local families. Local Aboriginal community-controlled organisations (or Aboriginal Medical Services) can also be contacted to ask about local protocols and how to follow them. It is important to engage key people in communities such as Elders and community leaders in the early stages, and respect their advice throughout the process.
NACCHO and its state affiliates, or state government Aboriginal and Torres Strait Islander health or policy units can provide advice early in the development process on communities or health centres that could be involved in any engagement process you undertake. Any need for an ethics application will also need to be made at this early stage.
It will also be critically important that correct and formal processes to attribute the source of the knowledge are adhered to and respected.
Specific engagement activities may require additional time and resources and will need to be factored into the project’s budget and timelines (see the Project planning, Consumer involvement and Engaging stakeholders modules). These activities could be very important to assure the successful uptake of the guideline, but must be planned for and undertaken appropriately.
Because Aboriginal and Torres Strait Islander communities are diverse, understanding the views of communities is likely to have direct implications on timing and resourcing. For example, seeking the views of community members may involve travel to remote regions. Or if you are working with people whose first language is not English, securing a qualified interpreter will be essential, but may be challenging as qualified interpreter services for some Aboriginal languages are scarce. These activities need to be incorporated into your budget and project plan.
Research translation strategies should consider the diversity of Aboriginal and Torres Strait Islander Peoples, including communities living in urban or remote areas, varying levels of English or differing levels of access to technology. In partnership with Aboriginal and Torres Strait Islander community or health care representatives, it is important to find ways to translate recommendations into culturally accessible material that can be used in different health settings such as primary health care and community settings or tertiary settings.
Examples of communication options can take the form of printed materials, videos, podcasts and apps:
Where feasible, the ‘voices’ of Aboriginal and Torres Strait Islander Peoples consulted in the development of the guideline should be heard. This can be through inclusion of quotes, case studies, interviews or formal recognition of who was consulted during the guideline development process. An example of this is Kidney Health Australia’s (KHA) yarning consultations.
It is important to celebrate success and share the many positive and successful initiatives in Indigenous Health at national levels (for example the National Aboriginal and Torres Strait Islander Cancer Framework (2015)) and at local levels (for example Success stories in Indigenous Health). This helps to build knowledge, inspire others and counteract the prevailing deficit discourse.
Sharing the results with other communities, organisations, policymakers and funding bodies may be done in many ways: through community meetings, stakeholder meetings, conference presentations, radio interviews, media articles and publications in journals.
The Central Australian Rural Practitioners Association's (CARPA) Remote Primary Health Care Manuals are examples of advice developed for remote communities by practicing remote health clinicians, using a ‘by the user for the user’ model. CARPA have developed a women’s business module that is a ‘Standard Treatment Manual for Women’s Business’.
Since 2002, NHMRC, the Canadian Institutes of Health Research (CIHR), and the Health Research Council of New Zealand (HRC) have been signatories to a tripartite agreement to improve Indigenous Peoples’ health. The Agreement commits the three agencies to working to improve the health of Indigenous Peoples through the sharing of best-practice, information, and expertise. The 2017 Tripartite Agreement intends to:
Building up best-practice, easily accessible evidence that can be modified to suit the local context is essential for organisations working to address health issues amongst their communities.
*Throughout this module, the word ‘Peoples’ is used when specifically referring to Aboriginal and Torres Strait Islander groups, and the word ‘people’ is used when referring to Aboriginal and Torres Strait Islander individuals. As these are the preferred terms, other terms such as ‘First Nations’ and ‘First Peoples’ will not be used in this guideline. When quoting from other sources or referencing published works, the original usage in the source is retained. (For more information see Keeping research on track II 2018).
Kidney Health Australia CARI Guidelines (Chronic Kidney Disease, Dialysis, Transplant Guidelines)
NHMRC. Consensus-Based Clinical Guideline for the Management of Volatile Substance Use in Australia
Department of Health. Pregnancy care guidelines. 2019
Royal Australian College of General Practitioners. National Guide to a preventative health assessment for Aboriginal and Torres Strait Islander people: 4th edition. 2024
Centre for Remote Health CARPA Standard Treatment Manual 8th Edition 2022, reprinted 2025
National Aboriginal and Torres Strait Islander Cancer Framework (2015)
The Optimal Care Pathway for Aboriginal and Torres Strait Islander people with cancer (2024)
Australian Indigenous Psychologists’ Association
SNAICC — peak body representing Aboriginal and Torres Strait Islander children
Public Health Association of Australia (Special Interest Group on health issues relating to Aboriginal and Torres Strait Islander People)
Perinatal Society of Australia and New Zealand
POCHE Indigenous Health Network
Central Australian Academic Health Science Network — a partnership of health services, health/medical research organisations and educational institutions in Central Australia
Department of Health. (2013) National Aboriginal and Torres Strait Islander Health Plan 2013-2023
Kanyini, a short documentary, describes the connection between Country, spirituality and wellbeing (pay to access)
Queensland Health. (2014). Aboriginal and Torres Strait Islander Patient Care Guideline
Reconciliation Australia. (2017). "Welcome to and Acknowledgement of Country"
Victorian Aboriginal Community Controlled Organisation (VACCHO). Cultural Safety Services
Getting it right: partnerships for change, describes Aboriginal and Torres Strait Islander knowledges and how different these systems of knowledge (or Ailan Kastom — Island Custom — in the Torres Strait) are to a western framework of understanding (Zubrzycki, Green et al. 2014).
Australian Indigenous HealthInfoNet (Includes a list of Cultural security, safety and awareness courses)
National Indigenous Television (NITV)
First Australians (SBS)
National Disability Insurance Agency (NDIA). Aboriginal and Torres Strait Islander Engagement Strategy (NDIS. 2017)
National Health and Medical Research Council (NHMRC). (2018) Keeping Research on Track II
Royal Australian College of General Practitioners (RACGP) An introduction to Aboriginal and Torres Strait Islander health cultural protocols and perspectives (RACGP and NACCHO. 2012)
The Lowitja Institute (2021). Knowledge Translation
QLD Department of Aboriginal and Torres Strait Islander Policy and Development. (1998)
South Australia Health. (n.d.) Aboriginal Community and Consumer Engagement Strategy
Working with Aboriginal Peoples and Communities: a practice resource
Ball, R. (2015). 'STEM the gap: Science belongs to us mob too.' Australian Quarterly 86(1): 13-19.
Ngaanyatjarra Pitjantjatjara Yankunytjatjara Women's Council (2019) Ngangkari — Traditional Healers.
The Lowitja Institute (2021). Knowledge Translation.
NHMRC would like to acknowledge and thank Associate Professor Catherine Chamberlain, Associate Professor Yvette Roe and Professor Jonathan Craig for their contribution as editors to the development of this module.
NHMRC also acknowledges the valuable input from its Principal Committee Indigenous Caucus (PCIC): Professor Sandra Eades, Professor Yvonne Cadet-James, Dr John Gilroy, Associate Professor Dan McAullay, Dr Odette Pearson, Associate Professor Yvette Roe, Dr Sean Taylor and Dr Laura Thompson.
ISBN: 978-1-86496-024-2